Child Assessment Forms for ABA: Digital Workflow Best Practices
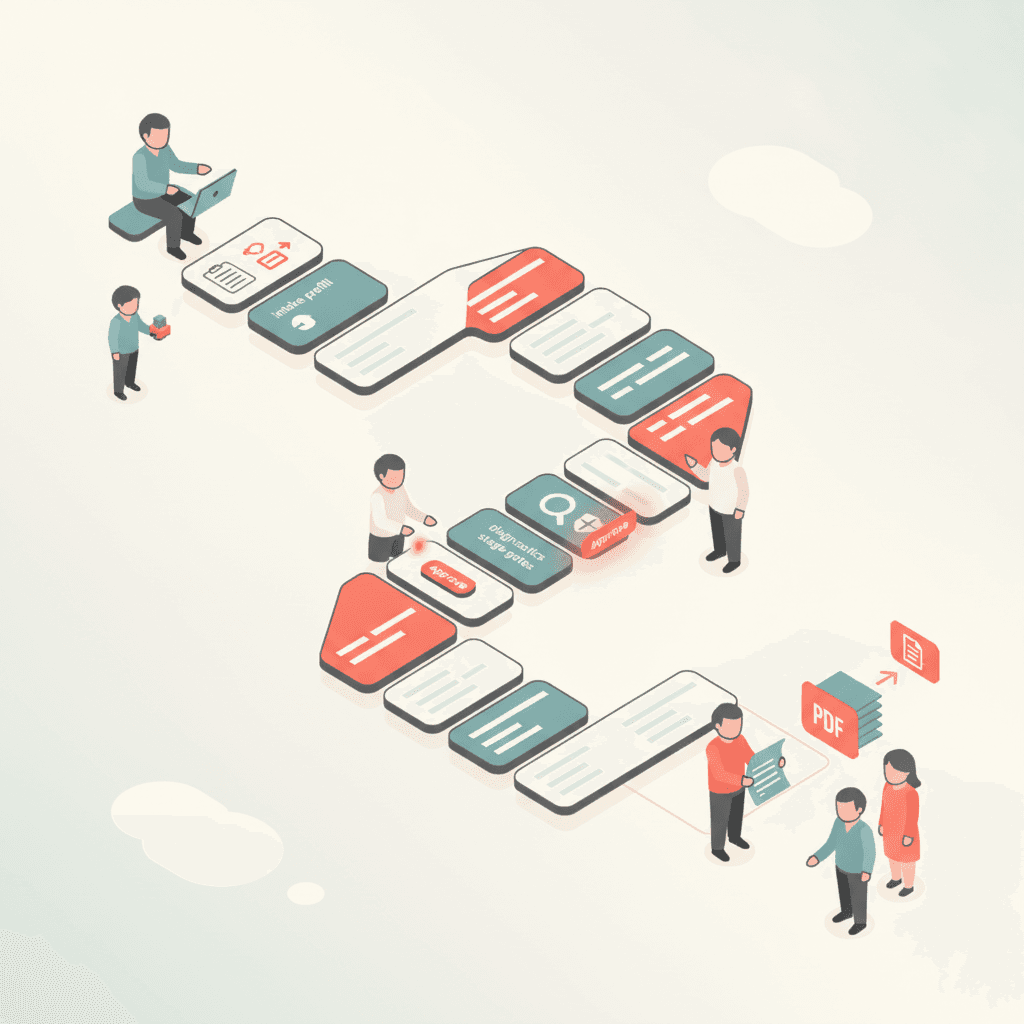
ABA child assessment form best practices—14-section digital workflow, intake prefill, diagnostics stage gates, and PDF export so POC authors use one record.
An ABA child assessment form is the bridge between a referral fax and a defensible Plan of Care. When the assessment lives in a shared drive, POC authors rewrite developmental history from memory. When it lives on the client record in a fourteen-section digital workflow, FBA summaries, ADOS-2 reports, and skill goal baselines cite the same facts payers will compare later.
This article covers best practices for digital child assessments at ABA centers: section design, prefill, diagnostics-stage ownership, and handoff to POC—without treating a form as a substitute for clinical judgment.
What is an ABA child assessment form?
An ABA child assessment form is a structured clinical document capturing biopsychosocial and developmental information used to justify ABA treatment: history, current functioning, strengths and needs, behavior concerns, caregiver context, and a summary that feeds medical necessity and goal setting. In multi-section software, each section maps to fields exportable to PDF and visible to BCBAs drafting the Plan of Care.
Why fourteen sections beat one long narrative
Long Word narratives encourage copy-paste from old cases and hide missing elements. Sectioned forms make gaps obvious—empty educational history stands out before signature. TargetFlo's child assessment model uses approximately fourteen sections spanning identifying data through clinical summary, matching how BCBAs think through case formulation.
| Section theme | POC connection |
|---|---|
| Identifying and referral | Section 3.x referral alignment |
| Developmental and medical history | Section 4.x assessment foundation |
| Education and current services | Schedule and concurrent services |
| Behavior and safety | FBA and BIP precursors |
| Summary and recommendations | Medical necessity and goals |
Explore product positioning on ABA child assessment forms for field-level detail.
Best practice 1: Create the record at intake, assess at diagnostics
Guardian contact and eligibility belong in early intake stages. The full child assessment belongs in diagnostics, when clinicians have records, interviews, and structured tools such as ADOS-2 underway. Starting the assessment earlier produces stale sections; starting later delays POC.
Configure your intake pipeline so coordinators see diagnostics tasks—assessment assigned, ADOS scheduled, documents collected—on one referral card.
Best practice 2: Prefill without blind trust
Prefill demographics, guardian names, referral source, and insurance product from intake. Clinicians must confirm accuracy at the visit—especially custody, preferred language, and school placement. Prefill reduces duplicate entry; it does not remove validation.
Duplicate data entry across intake and assessment is a top reason BCBAs resist new software. Fix the integration, not the clinician.
Best practice 3: Link ADOS-2 and assessment narratives
Medicaid and many commercial payers compare diagnostic instruments to the written assessment. When ADOS-2 lives in separate software, examiners retype conclusions into the child assessment summary.
Keep ADOS-2 on the same client record and reference instrument dates and conclusions in assessment section summaries—see ADOS-2 report software for structured reporting that exports alongside the assessment PDF.
Best practice 4: Assign owners and due dates
Diagnostics stage leaks when "the team" owns the assessment but no one is named. Assign a licensed clinician owner, a due date, and a pipeline checkpoint for partial completion if your center uses week-by-week diagnostics tracking.
Best practice 5: AI assist for empty sections only after facts exist
Assistive AI can draft section text from structured notes clinicians enter—never from guesses. Policy should require review before signature, same as ADOS-2 narratives. AI accelerates documentation; it does not replace interviews, record review, or standardized tools.
Best practice 6: PDF export and POC handoff
When assessment is finalized, export PDF to the record and mark the diagnostics checklist complete. POC authors should open assessment sections while writing medical necessity and skill baselines—not a stale export from three weeks prior.
For Medicaid centers, alignment with Medicaid POC standards educational content helps coordinators verify assessment foundation language before authorization upload.
Best practice 7: External examiners and consent
Some centers use external psychologists or volunteer examiners. External provider access with consent gates lets guest clinicians complete assigned sections without exposing unrelated caseload data—similar patterns to external ADOS completion described in center operations guides.
Table: digital vs paper assessment workflow
| Step | Paper-heavy center | Digital workflow |
|---|---|---|
| Intake capture | Fax and spreadsheet | Client record with prefill |
| Interview notes | Legal pad scanned later | Section fields same day |
| ADOS-2 | Separate template | Linked report on record |
| QA | Coordinator rereads PDF | Section completeness flags |
| POC start | Email attachments | Same-record authoring |
Measuring success
Track median days from diagnostics entry to signed assessment, percentage of assessments with all sections complete at signature, and authorization rework tagged "assessment incomplete." Operations leaders should review monthly with clinical directors—not only intake volume KPIs.
Language access and caregiver input
Assessment quality improves when sections capture preferred language, interpreter use, and who provided historical information. Document whether the primary interview was with one caregiver or multiple guardians—school teams and payers ask. Digital forms can prompt for these fields instead of leaving them to free memory at POC time.
Offer portal or interview pathways for caregiver questionnaires where your clinical policy allows, then merge responses into the assessment summary after clinician review. Caregiver words should never flow straight to payer PDFs without BCBA synthesis.
Revisions after signature
School placements change. New evaluations arrive mid-diagnostics. Version the assessment when material facts change rather than silently editing a signed PDF. Intake should see that a new clinician signature is required before POC authors cite updated baselines—same discipline you apply to revised Plans of Care.
Book a demo
See fourteen-section assessments, prefill from intake, diagnostics stage tasks, and PDF export in one workflow. Book a Demo with your diagnostics and intake leads together.
Educational content only; not legal or billing advice. Assessment content and instruments must match your clinical policies and payer contracts.
- ABA child assessment form
- child assessment workflow
- ABA diagnostics intake
- clinical documentation ABA
See it in TargetFlo
Move intake out of the fax inbox
Book a 30-minute demo and we’ll map your referral flow to the 9-stage pipeline, connect your fax provider, and show eligibility checks at intake.
Book a DemoFAQ