Medicaid POC Reauthorization for ABA: Documentation That Payers Expect
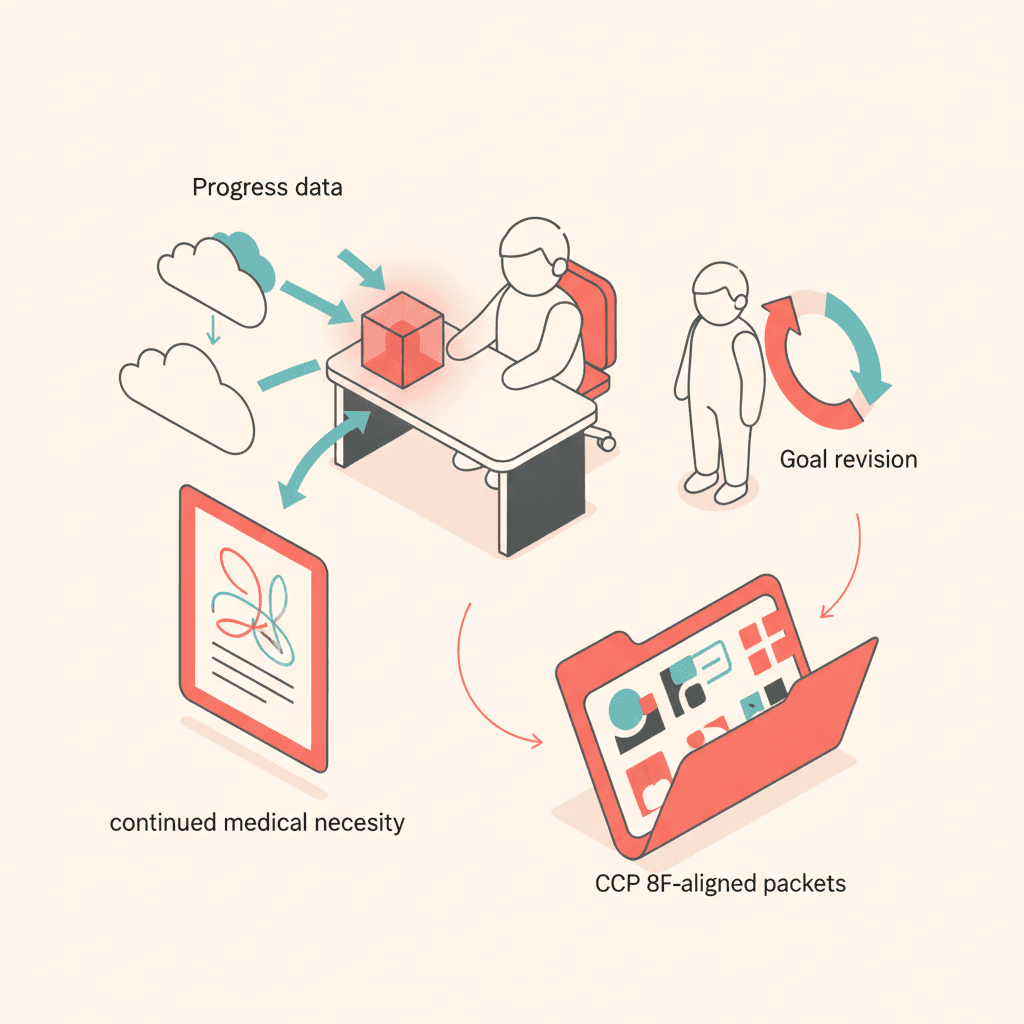
Medicaid POC reauthorization ABA guide: progress data, continued medical necessity, goal revision, and CCP 8F-aligned packets payers review at episode end.
Medicaid POC reauthorization for ABA is where authorized hours meet reality: did skill goals move, did behavior plans work, is medical necessity still documented, and does the next Plan of Care match what therapists actually delivered? Centers that treat reauth as "copy the initial POC and change the date" see avoidable pendings and clinical rework. Payers compare progress data to goals authorized last period.
This guide explains what strong reauthorization documentation includes, how it differs from initial and revised POCs, and how operations teams package submissions without promising guaranteed approval.
What is Medicaid POC reauthorization for ABA?
Medicaid POC reauthorization for ABA is the structured renewal request at episode end: an updated Plan of Care labeled for reauthorization, evidence of progress on prior goals, continued medical necessity narrative, and attachments payers specify—often including signed plans, data summaries, and supervision documentation. In North Carolina, CCP 8F checklist sections for reauth overlap initial requirements but emphasize outcomes and continued need.
Label the POC type correctly
Submission controls should mark reauthorization explicitly. Reviewers route initial and reauth packets differently; mislabeled types delay matching member files. Align internal training with Medicaid POC standards section 1.x guidance on POC type and dates.
Progress data that tells a story reviewers can scan
Data tables beat adjectives. For each authorized skill goal, show baseline at last authorization, current performance, and mastery status. For behavior reduction targets, show trend direction, intervention fidelity notes, and whether BIP strategies changed.
| Evidence type | Why it matters |
|---|---|
| Goal progress table | Links hours to outcomes |
| Graphs or trend summaries | Quick visual for reviewers |
| Session attendance vs authorized hours | Explains under-utilization |
| Caregiver training logs | Supports section 10.x commitments |
Pull source data from your clinical data collection practice; software should let BCBAs embed summaries into Plan of Care reauth sections without retyping from spreadsheets.
Continued medical necessity narrative
Medical necessity for reauth must answer: what risks remain if services stop, why current intensity is appropriate, and how progress—or lack of progress— informs the next period's plan. Regression after partial mastery, new settings, or co-occurring conditions belong here honestly.
Avoid boilerplate paragraphs identical to the initial POC. Reviewers compare files.
Goal revision: retire, revise, or add
Reauthorization is not only continuation. BCBAs should:
- Mark mastered goals complete with dates
- Revise goals with stale baselines
- Add goals tied to new assessment or school feedback
- Align behavior reduction targets to current FBA if functions shifted
Behavior plans that no longer match classroom or home contexts need updated BIP language before signature.
Signatures and family engagement
Reauth POCs typically require clinician signature and guardian attestation when plan content changes materially. Parent portal workflows speed re-signature when goals or hours shift—same clinician-first rules as initial plans on parent signatures.
Coordination with billing and authorization staff
Authorization coordinators need the signed reauth POC, progress attachments, and consistent CPT hour requests before submission. Misalignment between authorized units on the plan and billing tables triggers post-enrollment fixes.
Start reauth preparation thirty to forty-five days before authorization end—not the week units expire.
CCP 8F checklist mindset for reauth
Map reauthorization packets to section IDs: assessment foundation updates in 4.x, FBA and BIP in 5.x and 9.x, staffing in 11.x, data in authorization sections. A section-based QA pass catches missing graphs or outdated ICD-10 headers before upload.
Educational mapping lives on Medicaid POC standards; your compliance lead owns interpretation of NC Medicaid CCP 8F policy amended August 1, 2026 and clarification August 31, 2026.
AI assist on reauth narratives
Assistive AI can draft continued medical necessity or progress summary prose from clinician-entered metrics. Clinicians must verify numbers and clinical conclusions before sign. AI does not submit reauth packets autonomously and does not guarantee Medicaid approval.
Operational KPIs for reauthorization
Track percent of reauth packets submitted before authorization end date, pend rate on reauth vs initial, and BCBA hours spent per reauth package. Improvement in the first metric usually follows checklist QA, not more weekend work.
When progress is uneven across goals
Not every goal moves on the same curve. Reauth narratives should explain partial progress, plateaus, and regressions with equal honesty. If behavior reduction worsened during a school transition, document the updated FBA summary and BIP changes rather than repeating last period's strategies. Reviewers respect clear clinical reasoning more than uniformly positive adjectives.
Supervision and staffing documentation at reauth
Section 11.x-style expectations often resurface at reauthorization: supervising BCBA credentials, treatment team roles, and whether authorized hours match supervised delivery. Operations should confirm employee records on the POC match schedulers' reality before upload—especially after staff turnover mid-episode.
Discharge planning even when requesting more hours
Reauthorization packets benefit from explicit discharge or step-down criteria even when you are requesting continued intensive ABA. Payers want to see a clinical path—not an open-ended authorization. Document measurable criteria that would trigger fade plans or caregiver-led maintenance.
Internal timeline template
| Weeks before auth end | Action |
|---|---|
| 6 | BCBA reviews goal data with RBT leads |
| 4 | Draft reauth POC sections in software |
| 3 | Clinician sign; parent portal signature if needed |
| 2 | Authorization coordinator assembles attachments |
| 1 | Submit; track payer acknowledgment |
Adjust intervals to your state portal behavior; the principle is no single hero week where everything happens last minute.
Book a demo
Walk through reauthorization POC type, progress sections, signatures, and intake pipeline checkpoints on a sample case. Book a Demo with clinical and authorization staff together.
Educational content only; not legal or billing advice. Medicaid rules vary by state plan and amendment; verify requirements with your compliance advisor.
- Medicaid POC reauthorization ABA
- ABA reauthorization
- Medicaid POC standards
- CCP 8F reauth
See it in TargetFlo
Move intake out of the fax inbox
Book a 30-minute demo and we’ll map your referral flow to the 9-stage pipeline, connect your fax provider, and show eligibility checks at intake.
Book a DemoFAQ